The Complete Guide to Loading Bone After 40: What Actually Signals Growth
Quick Answer: Bone responds to three signals: high load magnitude, high rate of loading, and unfamiliar directions of force. Walking and cycling provide none of them adequately. An effective bone-loading week for a woman over 40 combines heavy resistance training twice weekly at loads above roughly 80 percent of maximum, brief impact work of 40 to 50 landings on most days, and sufficient protein, calcium, and vitamin D to build with.
The advice most women get about bone health - walk more, drink milk, take a calcium supplement - is not wrong so much as radically insufficient. Bone is living tissue that remodels continuously in response to mechanical signals, and the signals it responds to are specific.
This is the long version: what bone actually is, what it responds to, why the usual advice underdelivers, and what a genuinely effective week looks like at 40, 50, and 60.
This is general information, not medical advice. If you have diagnosed osteoporosis, a prior fragility fracture, or spinal conditions, the loading recommendations here need to be adapted with a physiotherapist or your clinician before you start - particularly anything involving spinal flexion or impact.


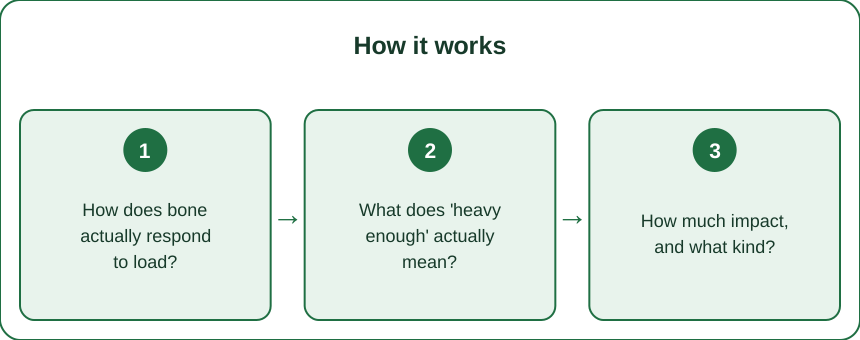
How does bone actually respond to load?
Bone is not inert scaffolding. It’s a metabolically active tissue that’s continuously dismantled and rebuilt, and the rate of each depends heavily on the mechanical signals it receives.
The remodelling cycle. Specialised cells called osteoclasts break down old bone; osteoblasts build new bone in its place. In a healthy adult these roughly balance. After menopause, the balance tips - declining oestrogen increases osteoclast activity, and bone loss accelerates markedly, with the most rapid loss in the first several years around and after the menopausal transition.
How bone senses load. Embedded within bone are osteocytes, cells sitting in tiny fluid-filled spaces. When bone deforms slightly under load, fluid moves past these cells, and that fluid movement is the signal that triggers remodelling toward more bone. The key insight is that bone responds to deformation, not to effort. A hard workout that doesn’t meaningfully deform bone produces no signal, however tired you are afterward.
The three properties that determine the signal:
-
Magnitude. The load has to exceed the range bone experiences during normal daily activity. Bone is already adapted to walking around; walking around more doesn’t change the message.
-
Rate. How quickly the load is applied matters as much as how large it is. A rapid load produces more fluid movement than the same load applied slowly - which is why brief impact is disproportionately effective relative to its size.
-
Novelty and direction. Bone adapts to the specific directions in which it’s loaded, and it habituates. The same stimulus repeated indefinitely produces diminishing response, which is why varied loading directions outperform high volumes of one thing.
Saturation is the fourth principle, and it’s the most practically useful. The bone-building response saturates rapidly - the first handful of loading cycles produce most of the effect, and further repetitions add little. This means 10 jumps three times a day beats 100 jumps once, and it means bone work can be genuinely brief. Rest between bouts restores sensitivity.
Why don’t walking and swimming build bone?
Because neither delivers the signals described above, and understanding why makes the alternatives obvious.
Walking. Ground reaction forces in walking are roughly 1 to 1.2 times bodyweight - which is precisely the load bone is already fully adapted to. Walking maintains what you have and is genuinely valuable for cardiovascular health, balance, and general function. It does not build bone in adults, and studies of walking programs in postmenopausal women consistently show minimal effect on bone density at the hip and spine.
Swimming and cycling. Both are non-weight-bearing. Swimmers and cyclists as athlete populations often show lower bone density than land-based athletes and sometimes lower than sedentary controls. Excellent exercise for many purposes. Not bone-building exercise, and cyclists specifically should treat bone loading as a separate necessary activity.
Light resistance training. Three sets of 15 with a weight you could do 25 with produces muscular endurance adaptations without approaching the load threshold bone needs. This is the gap most people fall into - they are lifting, and it isn’t heavy enough to count.
Yoga and Pilates. Improve balance, posture, and muscular control, all of which reduce fall risk substantially - and fall prevention genuinely reduces fracture risk. But the loading magnitude is low. Some spinal flexion positions are also specifically contraindicated for people with existing vertebral fragility, which is worth knowing before assuming a gentle practice is automatically safe.
What does work, in descending order of evidence: heavy progressive resistance training, high-impact loading such as jumping and hopping, and multidirectional loading including changes of direction. Programs combining heavy resistance with impact have shown the most consistent improvements in bone density at the hip and spine in postmenopausal women.
What does ‘heavy enough’ actually mean?
Specific numbers, because ‘heavy’ is the vaguest word in fitness.
The load threshold. Meaningful bone response generally requires loads above roughly 80 to 85 percent of your one-rep maximum - which in practical terms means sets of about 5 or fewer repetitions where the last rep is genuinely hard.
How to find that without testing a true maximum: use a rate of perceived exertion scale. A set of 5 that leaves you with one repetition in reserve is approximately the right zone. If you finish a set of 5 and could confidently do 5 more, the weight is too light for this purpose.
The exercises that matter most, because bone adapts locally where it’s loaded, and the clinically significant fracture sites are hip, spine, and wrist:
- Deadlift - loads spine and hip directly, the two most consequential sites
- Squat or leg press - hip and spine, with the barbell back squat loading spine more directly
- Overhead press - loads spine axially and stresses the wrist and forearm
- Loaded carries - farmer’s walks load spine and hip under a long time-under-tension with a gait pattern
- Row and pull-up variants - upper spine and the muscular support of thoracic posture
The progression that matters. Bone adapts to increasing load, so the weight has to climb over months. A program with the same weights in month six as in month one has stopped being a bone program. Add small increments regularly - even 2.5 pounds per session on lower body lifts accumulates substantially over a year.
On safety and technique. Heavy lifting is well tolerated by older adults and by postmenopausal women in supervised trials, including in those with low bone density. The caveat that genuinely matters is loaded spinal flexion - deadlifting with a rounded back, or weighted crunches - which is the pattern associated with vertebral compression risk. Learn the hinge with a coach if you possibly can. This is the single best investment in the whole program.
How much impact, and what kind?
Impact is the other half, it’s the half people skip, and it takes almost no time.
Why impact works. Ground reaction forces in jumping and landing reach 3 to 6 times bodyweight, applied very rapidly. That combination of magnitude and rate is exactly what the osteocyte network responds to, and hopping and jumping programs have shown improvements in hip bone density in premenopausal and early postmenopausal women.
The dose, based on the saturation principle:
- 40 to 50 landings per session
- Most days of the week
- Split into two or three short bouts with several hours between them if convenient - this exploits the resensitisation effect
- Total time: about two minutes a day
A progression from a genuine starting point:
Weeks 1-2 - foundation. Heel drops: rise onto toes, drop heels firmly to the floor. 2 sets of 10, twice daily. Low impact, appropriate for almost everyone, and a legitimate stimulus.
Weeks 3-4. Add small hops in place, 2 sets of 10, landing softly through the whole foot.
Weeks 5-8. Progress to jumps with a fuller landing, 3 sets of 10, plus hopping side to side and forward and back to vary direction.
Beyond week 8. Add single-leg hops, step-downs from a low box, and skipping. Multidirectional beats vertical-only because bone adapts directionally.
Who should not do impact loading: anyone with diagnosed osteoporosis or a prior fragility fracture without clearance, and anyone with significant hip or knee joint pathology. For those groups, heavy resistance training remains appropriate and is the more important half anyway - and low-level options like heel drops may still be suitable with clinical guidance.
On surface and footwear: a firm surface transmits more of the load to bone than a heavily cushioned one. Do this on a hard floor in flat shoes or barefoot, not on a thick gym mat in maximally cushioned trainers - the cushioning absorbs precisely the signal you’re trying to create.

What do you need to eat to build with?
Mechanical signal tells bone to build. Nutrition determines whether the materials are available.
Protein - more important than it’s given credit for. Roughly half of bone volume is protein matrix, largely collagen. Higher protein intakes are associated with better bone density and lower fracture risk, and the old concern that protein leaches calcium from bone has not held up.
- Target: roughly 1.2 to 1.6 grams per kilogram of bodyweight daily, more at the upper end if you’re training hard
- Distribute it across meals - roughly 25 to 30 grams per meal is more effective than the same total in one sitting
- This is the nutrient most commonly under-consumed by active women over 40, often by a wide margin
Calcium. Around 1,000 to 1,200 mg daily for women over 50. Food sources are preferable to supplements - dairy, tinned fish with bones, fortified plant milks, tofu set with calcium, leafy greens other than spinach. Very high supplemental doses have not shown clear fracture benefit and have raised cardiovascular questions.
Vitamin D. Required for calcium absorption, and insufficiency is common - particularly at higher latitudes from autumn onward, when skin synthesis effectively stops. Testing is worthwhile rather than guessing, since both deficiency and excessive supplementation are undesirable.
Others that matter: vitamin K2, magnesium, and adequate overall energy intake. Chronic under-eating is genuinely bad for bone - low energy availability suppresses the hormonal environment that supports bone formation, which is why bone density problems appear in young athletes as well as older women.
What harms bone: smoking, heavy alcohol intake, prolonged corticosteroid use, and prolonged inadequate energy intake. The first two are the modifiable ones for most people.
What Nobody Tells You About Bone After 40
Six things that change how you’d approach the whole project.
The perimenopausal window is the highest-leverage period there is. Bone loss accelerates sharply in the years around the final menstrual period, and this is the point at which loading has the most to protect. Waiting for a DEXA scan at 65 to show a problem means missing the window where prevention is most effective. Starting a loading program in your forties is worth considerably more than starting the same program in your sixties.
Bone density changes slowly - plan in years. Detectable change on a DEXA scan typically requires 12 to 24 months. The absence of a visible result at six months means nothing. This is a project with a multi-year horizon and no short-term feedback, which is exactly why it needs to be built into a routine rather than pursued as a burst of motivation.
Maintaining is a real and worthwhile outcome. Much of the literature in postmenopausal women shows maintenance or small gains rather than large increases. Against a background of ongoing age-related loss, holding steady is a genuine win - the comparison isn’t to your thirties, it’s to what would have happened otherwise.
Muscle and bone are linked. Muscle pulls on bone, and that pull is one of the largest loads bone routinely experiences. Building muscle mass builds bone through the same sessions, and losing muscle mass through inactivity or under-eating removes that pull.
Falls matter as much as density. Most fragility fractures involve a fall. Balance training, ankle and hip strength, and reaction time reduce fracture risk through a completely separate mechanism, and they’re worth including for that reason alone. Single-leg balance work costs a minute a day.
HRT is a legitimate part of the conversation. Hormone therapy has well-documented effects on bone density in postmenopausal women, and for many it’s a reasonable component alongside loading. That’s a discussion with a clinician who knows your history - the relevant point is simply that exercise and medical options aren’t in competition.
What does a full week look like?
Three versions, by decade. Each assumes no existing diagnosis; adapt with a clinician if you have one.
In your 40s - build aggressively while the window is open
- Monday: Heavy lower body. Deadlift 4 sets of 5, squat 3 sets of 5, split squat 3 sets of 8 per leg, farmer’s carry 3 sets of 30 metres
- Tuesday: Impact bout (2 min) + walk or easy cardio
- Wednesday: Heavy upper body. Overhead press 4 sets of 5, row 4 sets of 5, pull-up progression 3 sets, wrist and grip work
- Thursday: Impact bout + balance work (single-leg stands, 3 x 30 seconds per side)
- Friday: Full body heavy. Deadlift variant 3 sets of 5, front squat 3 sets of 5, press 3 sets of 5
- Weekend: Something outdoors with varied terrain - hiking loads bone multidirectionally and is genuinely enjoyable
- Daily: brief impact bout, protein at every meal
In your 50s - the same structure, more recovery
Two heavy sessions rather than three, with an extra day between them. Keep the load heavy - this is the decade where people reduce weight and increase reps, which removes the entire stimulus. Impact continues daily unless contraindicated. Add a dedicated balance session.
In your 60s and beyond - heavy is still the answer, technique is the constraint
Heavy resistance training remains effective and well tolerated in this age group. Progress more slowly, warm up longer, and get coaching on the hinge. Impact may need to be reduced to heel drops and low hops depending on joint health and bone status. Balance and fall prevention become proportionally more important than they were at 45.
Across all three: the non-negotiables are loads heavy enough to be genuinely hard at 5 reps, progression over months, some form of impact if it’s safe for you, adequate protein, and the patience to run it for years rather than weeks.
FAQ: Bone Loading Questions, Answered
I already have osteopenia. Is heavy lifting safe?
Supervised progressive resistance training has been studied in women with low bone mass and has generally been well tolerated with appropriate technique and supervision. The pattern to avoid is loaded spinal flexion. Get an assessment and ideally some coaching before starting, rather than avoiding loading entirely - avoidance is its own risk.
How do I know if it’s working without a DEXA scan?
You largely don’t, in the short term, which is the frustrating part. Track the proxies you can measure: the weight on the bar going up, jump quality improving, balance holding steady. Those correlate with the stimulus even when you can’t measure the outcome.
Does weighted vest walking count?
It’s better than unweighted walking and it’s not a substitute for heavy loading. A vest at 10 percent of bodyweight adds meaningfully to the load, but you’re still in the range near everyday activity rather than well above it. Useful as an addition, not as the main event.
Is it too late to start at 65?
No. Resistance training improves bone density, muscle mass, strength, and balance in adults well into their seventies and eighties. The gains may be smaller than they’d have been at 45, and the fall-prevention benefit alone justifies the training regardless.
How long between heavy sessions?
At least 48 hours for the same movement pattern. Bone’s mechanosensitivity resensitises within hours, but muscle and connective tissue recovery sets the practical limit, and technique degrades when you’re under-recovered.
TL;DR:
- Bone responds to load magnitude, loading rate, and novel directions - not to effort or duration
- Walking, swimming, and light resistance training don’t provide any of the three
- Heavy means sets of 5 or fewer where the last rep is genuinely hard, progressed over months
- Impact: 40-50 landings a day, split into short bouts, about two minutes total
- Protein at 1.2-1.6 g/kg matters more than most people realise; calcium and vitamin D are the supporting cast
- The perimenopausal window is the highest-leverage period, and results take 12-24 months to measure
Bone is the one tissue where the standard advice most badly underdelivers. It doesn’t need more hours - it needs heavier loads, a couple of minutes of impact, and enough years of consistency to show up on a scan.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
