Your Bone Density Score, Decoded: What T-Scores and Z-Scores Actually Tell You
Quick Answer: A T-score compares your bone density to a healthy 30-year-old: -1.0 and above is normal, -1.0 to -2.5 is osteopenia, and -2.5 or below meets the definition of osteoporosis. A Z-score compares you to people your own age and matters most if you are premenopausal or under 50. Neither number measures bone quality, and a single scan tells you far less than two scans two years apart. Density explains roughly 60 to 70 percent of fracture risk - the rest comes from bone architecture, muscle strength, and whether you fall in the first place.
The report arrives as a PDF with a shaded graph and a number that sounds like a grade. Most people read the number, feel either relieved or alarmed, and file it away. That is a waste of a good scan. The number is a starting coordinate, not a verdict, and the parts of the report people skip are usually the parts that should change what they do on Monday.


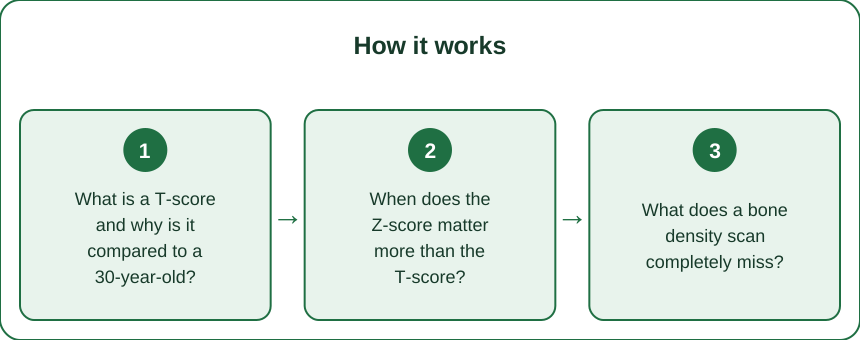
What is a T-score and why is it compared to a 30-year-old?
Peak bone mass happens somewhere between 25 and 30 for most people. That is the high-water mark - the densest your skeleton will ever be. Everything after that is a slow drift downward, faster during perimenopause, slower again afterward.
The T-score asks a simple question: how far are you from that peak, measured in standard deviations? A T-score of -1.0 means you are one standard deviation below a healthy young adult. A -2.5 means two and a half.
The World Health Organization thresholds are the ones your doctor uses:
- -1.0 and above: normal
- -1.1 to -2.4: osteopenia (low bone mass)
- -2.5 and below: osteoporosis
- -2.5 and below plus a fragility fracture: severe osteoporosis
These cutoffs are useful and slightly arbitrary at the same time. They were set to define a population for treatment trials, not to mark the exact point where your femur becomes fragile. Someone at -2.4 and someone at -2.6 are not meaningfully different people; they just fall on opposite sides of a line drawn by committee.
Why one number hides three sites
A standard DEXA scans the lumbar spine, the femoral neck, and often the total hip. You get a T-score for each. They frequently disagree, sometimes by a full point.
The spine is mostly trabecular bone - the spongy, honeycomb kind that turns over fast and responds fast. The hip is more cortical, the dense outer shell, which changes slowly. Estrogen loss hits trabecular bone first, which is why the spine number often drops first in the years around menopause.
Your diagnosis is set by the lowest of the sites. But the site-by-site pattern is the interesting part, and it is the part nobody reads out loud in a three-minute appointment.
When does the Z-score matter more than the T-score?
The Z-score compares you to people of your own age, sex, and often ethnicity. It answers a different question: are you unusual for your cohort?
For a 68-year-old, a T-score of -2.2 is expected and a Z-score of -0.2 confirms she is right where her peers are. For a 34-year-old, a T-score of -2.2 with a Z-score of -2.1 is a flag - she is well outside her age group, and something other than normal aging is likely driving it.
A Z-score at or below -2.0 is described as below the expected range for age, and it should trigger a look for a cause:
- Long-term corticosteroid use
- Low energy availability or a history of disordered eating
- Absent or irregular periods for extended stretches
- Celiac disease or other malabsorption
- Thyroid or parathyroid overactivity
- Certain medications, including some anticonvulsants and long-term proton pump inhibitors
If you are premenopausal or under 50, most clinical guidance says the Z-score is the number to read first. The T-score in that group can produce alarm that the underlying biology does not justify - or, occasionally, false comfort.
The ethnicity and calibration footnote
Reference databases differ between machines and between manufacturers. This is why a scan on a different machine in a different clinic is not directly comparable to your last one, even if both say GE or Hologic on the side. If you are tracking change over time, use the same machine when you possibly can. It is the single cheapest way to make your next scan actually mean something.
What does a bone density scan completely miss?
Density is mass per area. It says nothing about how that mass is arranged, and arrangement is a large part of why bone breaks or does not.
Think of two bridges built from identical tonnages of steel. One has an intact truss; the other has the same steel with several struts missing and the rest thickened to compensate. Same weight on the scale, very different behavior under load. Trabecular bone works the same way - once cross-struts are lost, they are not rebuilt, and the remaining structure carries load less efficiently no matter how dense it reads.
Things a standard DEXA cannot see:
- Trabecular architecture and connectivity
- Bone turnover rate - whether you are currently losing fast or holding steady
- Cortical porosity, which rises sharply in later decades
- Whether you have the leg strength and balance to avoid a fall
Some centers report a trabecular bone score (TBS), derived from the texture of the same lumbar spine image. It is an imperfect proxy for architecture, but it adds real information on top of density, and if your report has one, it is worth asking about.
FRAX and the risk you actually care about
Most reports include or can generate a FRAX score: a ten-year probability of major osteoporotic fracture and of hip fracture. It folds in age, prior fracture, parental hip fracture, smoking, glucocorticoids, rheumatoid arthritis, and alcohol intake alongside femoral neck density.
This is closer to the question you are asking. A T-score is an input; a fracture probability is an answer. Two people at -2.3 can have very different ten-year risks, and the treatment conversation should hinge on the second number, not the first.

How much change between scans is real change?
This is where most people misread their own progress, in both directions.
DEXA has a least significant change - the smallest difference that exceeds measurement noise. It varies by machine and technician, but a common working figure is roughly 3 percent at the spine and 5 percent at the hip. Anything smaller than that is not a trend. It is the machine, the positioning, the technologist, the fact that you stood differently.
So a scan showing you went from -2.1 to -2.2 has told you one thing: nothing changed. That is not failure. In the years around menopause, holding steady is a genuine result.
Practical implications:
- Do not rescan yearly unless there is a specific reason - you will mostly be measuring noise and generating anxiety.
- Two years is a reasonable interval for most people, one year if you are on high-dose steroids or newly started on treatment.
- Use the same machine. Cross-machine comparisons need a conversion nobody will do for you.
- Judge by direction over two intervals, not one gap.
The lag problem with training
Bone remodeling runs on a slow cycle - roughly three to four months from resorption to full mineralization of the new tissue. Add the fact that mineral density keeps rising in newly formed bone for months after, and the honest timeline for a training effect to show up on a scan is 12 to 24 months.
This is why loading programs get abandoned. Someone trains hard for eight months, scans, sees a number inside the noise band, and concludes it did not work. It may well have worked; the measurement just cannot resolve it yet. Judge the training by whether the loads are going up, not by whether the scan moved.
Myth vs Fact: five things people believe about bone scans
Myth: Osteopenia means you are on your way to osteoporosis.
Fact: Osteopenia is a wide band that covers a huge share of women over 50. Most people in it never fracture. It is a signal to load your skeleton and check the modifiable causes, not a countdown clock.
Myth: A good score means you can stop worrying about falls.
Fact: Most fractures happen in people who do not meet the osteoporosis threshold, simply because there are so many more of them. Balance and leg strength are protective regardless of your T-score, and they respond in weeks rather than years.
Myth: Calcium supplements will move the number.
Fact: Correcting a genuine deficiency helps. Adding calcium on top of an adequate intake does very little to density and has been linked to other issues at high supplemental doses. Food-first, roughly 1,000 to 1,200 mg daily total for most adults over 50, with vitamin D adequate enough for absorption.
Myth: Swimming and cycling count as bone-building exercise.
Fact: They are excellent for the heart and nearly silent for bone. Bone responds to impact and to high-magnitude, rapidly applied loads. Neither sport supplies them.
Myth: Once bone is lost, nothing can be done.
Fact: Progressive resistance training and impact loading have produced measurable density gains at the spine and hip in postmenopausal women in controlled trials - modest gains, but in the right direction, alongside large improvements in strength and balance. The ceiling is real; the floor is not where people assume.
What should you actually change after reading your report?
Convert the report into three decisions rather than one feeling.
Decision one: is there a cause to chase? If your Z-score is at or below -2.0, or your loss between scans is faster than expected, that is a workup conversation - vitamin D, calcium, thyroid, parathyroid hormone, celiac screen, medication review. Do not let a slow decline get written off as ordinary aging without a look.
Decision two: is the load in your week enough? Bone responds to strain magnitude and strain rate, not to duration. Two to three sessions a week of progressive resistance work at genuinely challenging loads, plus a short impact component, is the evidence-supported shape.
- Loaded hinges and squats in a 5 to 8 rep range, taken close to hard
- Overhead and rowing work for the upper spine
- 50 to 100 impacts a week - hops, jumps, or firm heel drops - split across sessions
- Progressive overload that you record, because unrecorded training drifts downward
Decision three: how likely are you to fall? This is the underrated one. Single-leg balance, reaction step drills, and enough ankle and hip strength to catch a stumble prevent more fractures than any density change you will achieve in the same period. A fracture requires a fall plus a fragile bone. You can work on both, and one of them improves in six weeks.
Check your medication list too. Sedatives, some blood pressure drugs, and anything causing morning dizziness raise fall risk in ways no scan captures.
FAQ: Bone Density Questions, Answered
Can my T-score get better, or only get worse?
It can improve. Trials of progressive resistance and impact training in postmenopausal women have shown small gains at the lumbar spine and femoral neck, typically 1 to 3 percent over a year or two - within or just above the noise band, which is why consistency over multiple years matters more than any single stretch. Medication produces larger changes when it is indicated.
Should I get a scan if I am in my thirties?
Usually not, unless you have a specific risk factor: long-term steroids, absent periods for six months or more, a history of low energy availability, an inflammatory or malabsorptive condition, or a fragility fracture. Routine screening in healthy premenopausal women mostly generates T-scores that get misinterpreted.
My spine score is much better than my hip. Which do I believe?
Diagnosis follows the lowest site, so the hip governs. But check the spine image first - degenerative changes, compression fractures, and arthritis all falsely inflate lumbar density in older adults. A spine score that looks suspiciously good in someone with known arthritis is often an artifact, and the hip is the more honest number.
This is general information, not medical advice. Bring your actual report to your own clinician - the site-by-site numbers, the Z-score, and any TBS or FRAX values are the parts worth discussing.
TL;DR:
- T-score compares you to a 30-year-old and sets the diagnosis; Z-score compares you to your own age group and matters most under 50.
- Your diagnosis follows the lowest site, but a spine score inflated by arthritis is a known artifact - the hip is usually the more honest number.
- Change between scans is only real if it exceeds roughly 3 percent at the spine, 5 percent at the hip. Rescanning yearly mostly measures noise.
- Density explains part of fracture risk. Architecture, muscle strength, and fall likelihood carry the rest - and the last one improves fastest.
Read the report as a map rather than a grade. It tells you where you are standing, which sites are drifting, and whether anything unusual is driving it. Then the useful work is the same for almost everyone: load the skeleton hard enough to matter, keep the impacts in the week, and make yourself very hard to knock over.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
