Why Walking Alone Does Not Build Bone - and What Actually Does
Quick Answer: Bone responds to strain that is higher than what it is used to, applied quickly. Walking produces forces your skeleton already handles thousands of times a day, so it maintains rather than builds. What does build bone is progressive resistance training taken to genuinely challenging loads, plus impact - hopping, skipping, or stair descent - in short bursts. Two to three sessions a week, sustained for at least six months, is the realistic prescription.
This is one of the most common misunderstandings in women’s health advice, and it costs people years. Walking is genuinely valuable and it is not doing the job people believe it is doing.


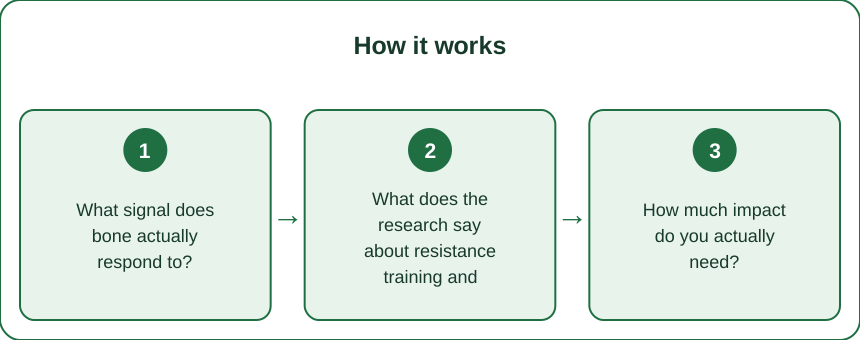
What signal does bone actually respond to?
Strain magnitude and strain rate - how hard, and how fast. Not duration, and not repetition.
Bone is living tissue that constantly remodels itself. Specialised cells break old bone down and others build new bone up, and the balance between them is heavily influenced by mechanical loading. The cells embedded within bone - osteocytes - detect deformation of the bone matrix and signal for more building when that deformation exceeds what they are accustomed to.
Three principles come out of decades of research on this:
1. The stimulus must exceed the habitual load. This is the crucial one. Your skeleton has already adapted to the forces of daily life, including walking. Repeating a familiar load, however many times, sends no signal that more bone is required. A load meaningfully above the usual is what triggers the response.
2. Rate matters as much as magnitude. Rapidly applied load produces a stronger osteogenic response than the same force applied slowly. A hop generates a fast-rising force; a slow walk does not. This is why impact activities show up so consistently in the research.
3. The response saturates quickly. Bone cells become less responsive within a fairly small number of loading cycles - roughly a few dozen. After that, more repetitions add fatigue without adding stimulus. Short bursts with rest between them are more effective than long continuous sessions, which is the opposite of how most people think about exercise volume.
What this means for walking specifically. Walking generates ground reaction forces of roughly one to one and a half times bodyweight. Your skeleton handles that several thousand times daily already. It is, by definition, the habitual load. Adding another 5,000 steps adds cardiovascular benefit, mood benefit, weight management benefit, and joint health benefit - all genuinely valuable - but it does not exceed the threshold your bone cells are monitoring.
Running is a different matter: it generates forces around two and a half to three times bodyweight with a much faster rise time, and it does appear in the research as bone-positive at the hip. Walking simply is not in the same category, and treating the two as interchangeable is where the confusion starts.
What does the research say about resistance training and bone?
It is the most consistently supported intervention, with two important caveats about load and site specificity.
The overall picture: reviews of resistance training trials in postmenopausal women generally find small but real improvements in bone mineral density at the spine and hip, typically in the range of one to three percent over programmes lasting six to twelve months, with better results in higher-intensity programmes. That sounds modest, and it is worth putting in context: untreated postmenopausal bone loss commonly runs at around one to two percent per year at some sites. Halting that decline and reversing it slightly is a meaningful outcome.
Caveat one: load intensity matters enormously. Light weights for high repetitions - the format most commonly recommended to older women - produces very little bone response. The trials that show the clearest results use loads in the range of 80-85% of maximum for sets of around five to eight repetitions. This is heavier than most people expect to be told, and it is the main reason so many well-intentioned programmes produce disappointing bone results.
The best-known trials in this area demonstrated that high-intensity resistance and impact training, supervised and properly progressed, was both effective and safe in postmenopausal women with low bone mass - including women who had been told to avoid heavy loading. Supervision and technique were central to that safety record.
Caveat two: bone adapts where it is loaded. This is site specificity, and it is why the exercise selection matters more than the total volume. Loading the legs does very little for the wrist. Loading the arms does nothing for the hip. If you are concerned about the three sites that matter most clinically - spine, hip, and wrist - your programme needs to load all three.
Which movements load which sites:
- Spine: squats, deadlifts, overhead press, loaded carries. Anything where the load is transmitted through an upright torso
- Hip: squats, lunges, step-ups, deadlifts, and impact work such as hopping
- Wrist: push-ups, planks, front-loaded carries, and any pressing movement where weight passes through the hand and forearm
The overhead press deserves specific mention because it loads the spine and the wrist simultaneously and is often missing from programmes written for bone health.
How much impact do you actually need?
Far less than most people assume - and the small dose is what makes it practical.
The counterintuitive finding: bone’s response to impact saturates after a small number of loading cycles. Adding hundreds more jumps to a session produces diminishing returns. The research consistently points toward brief, frequent, high-quality impact rather than prolonged sessions.
What a research-informed impact dose looks like:
- Around 10-20 hops or jumps, performed with a moment of rest between each so the tissue is not simply accumulating fatigue
- Done on most days, rather than piled into one long session weekly
- Landing matters. A hop where you land softly and absorb everything through bent knees deliberately reduces the rate of force. For bone purposes, a firm, controlled landing that lets the force transmit is the point
- Total time: under two minutes
Practical everyday versions:
- Hopping ten times on each leg while the kettle boils
- Skipping rope for 30 seconds, twice
- Descending stairs briskly - stair descent generates higher forces than ascent, and most people habitually take stairs down slowly
- Heel drops: rise onto the toes, then drop the heels firmly onto the floor. Twenty of these is a legitimate bone stimulus and requires no equipment or space
The critical safety boundary. Impact loading is appropriate for people with healthy bone or mild low bone density. It is not appropriate as a self-prescribed intervention for anyone with established osteoporosis, a history of fragility fracture, or vertebral compression fractures. In those situations the loading strategy needs to be built and supervised by a physiotherapist or exercise professional with specific training, because the risk profile is genuinely different.
Similarly, forward flexion of the spine under load - loaded sit-ups, weighted toe touches, deep forward bends with weight - is generally advised against for people with vertebral fragility, because compression at the front of the vertebral body is the mechanism of the most common osteoporotic fracture. This is one of the few areas of exercise advice where a specific movement is genuinely contraindicated for a specific population.

Myth vs Fact: Exercise and Bone Density
Myth: Walking 10,000 steps a day protects your bones. Fact: It supports cardiovascular health, weight management, mood, and joint health, all of which are real reasons to do it. For bone, walking generates a force your skeleton is already fully adapted to, so it maintains rather than builds. The studies looking specifically at walking interventions in postmenopausal women find little to no effect on bone mineral density at the hip or spine.
Myth: Light weights with high reps are safer and better for older women. Fact: They are safer in a narrow sense and substantially less effective for bone. The trials that produce meaningful bone changes use heavy loads for low repetitions, with supervision. The safety record of properly supervised high-intensity training in this population is good, and the cost of the low-intensity default is years of ineffective effort.
Myth: Swimming and cycling build bone because they are exercise. Fact: Both are excellent for cardiovascular fitness and joint-friendly, and both are non-weight-bearing. Studies of competitive cyclists and swimmers frequently find bone density no higher, and sometimes lower, than in non-athletes. If these are your primary activities, you need to add loading separately - this is one of the most important practical implications in this whole area.
Myth: Once you have osteoporosis, exercise is dangerous. Fact: Appropriate exercise is a core part of management, including resistance training. What changes is that it needs to be prescribed and supervised rather than self-directed, and certain movements are avoided. The risk of doing nothing - continued loss and reduced balance - is substantial.
Myth: Calcium supplements are the main thing. Fact: Adequate calcium and vitamin D are necessary for bone building, but they are the raw materials rather than the signal. Supplementing without loading gives your body materials with no instruction to use them. The interventions with the clearest effect on density are mechanical, and nutrition supports them rather than replacing them.
Myth: It is too late to start after menopause. Fact: The trials showing the clearest gains were largely conducted in postmenopausal women with low bone mass. The rate of loss is highest in the years immediately around menopause, which makes that window the highest-value time to start, not the point at which it stops mattering.
What does a realistic weekly programme look like?
Two to three resistance sessions plus a daily two-minute impact habit. Roughly 90 minutes a week in total.
Session structure - about 40 minutes, twice or three times a week:
Warm-up, 8 minutes. Five minutes of brisk walking or a bike, then 10 bodyweight squats, 10 arm circles each direction, and 5 slow lunges each side.
Main lifts, 25 minutes. Four movements, 3 sets each:
- Squat pattern - goblet squat or barbell back squat, 3 sets of 6-8
- Hinge pattern - Romanian deadlift or trap bar deadlift, 3 sets of 6-8
- Overhead press - 3 sets of 6-8. Loads the spine and the wrist at once
- Row or pull-down - 3 sets of 8-10, to keep the back balanced
Accessory, 7 minutes. Loaded carry, 3 sets of 30 seconds. Push-up variation, 3 sets to two reps short of failure - this is your main wrist loading.
What load actually means here. The final one or two repetitions of each set should be genuinely difficult while your technique holds. If you could do five more, the load is too light to be doing the job. This is the single most common failure point in bone-focused programmes - people follow the structure perfectly and never make the weight heavy enough.
Progression: add a small increment as soon as you can complete all three sets at the top of the rep range with good form. In practice that means increasing something roughly every one to two weeks in the first few months, then more slowly.
The daily impact habit: 20 heel drops or 10 hops on each leg, once a day, separate from the resistance sessions. Two minutes. This is the piece people skip and it is the cheapest item on the list.
Balance work, and why it belongs here. Bone density reduces fracture risk. Not falling reduces it far more. Two minutes of single-leg standing per side while brushing your teeth, progressing to eyes closed or on a cushion, addresses the other half of the equation. In terms of preventing an actual fracture, balance training is at least as valuable as density training, and it is frequently left out of articles about bone.
Timeline expectations. Bone remodels slowly. A full remodelling cycle takes several months, and meaningful density change is measured over six to twelve months at minimum. Scans repeated more often than annually generally cannot distinguish real change from measurement variation. Strength, on the other hand, will improve within weeks - use that as your short-term feedback and let the density follow.
What else moves the needle beyond exercise?
Four factors, in rough order of how much control you have over them.
Protein intake, which is underappreciated. Bone is roughly half protein by volume. Low protein intake is associated with lower bone density and higher fracture risk, and it also limits the muscle you can build - which matters because muscle pulls on bone and is part of the loading mechanism. A commonly cited target for older adults is somewhere around 1.0-1.2g per kilogram of bodyweight daily, higher than standard general recommendations. For many women that means adding a substantial amount to current intake, particularly at breakfast.
Calcium and vitamin D as raw materials. Typical recommendations for postmenopausal women sit around 1,000-1,200mg of calcium daily, ideally from food, and vitamin D sufficiency matters because it governs how much calcium you absorb. Vitamin D deficiency is common, particularly at northern latitudes through autumn and winter - which starts about now. Testing is straightforward and worth asking about at your next appointment.
Things that actively work against bone. Smoking is strongly associated with lower density and higher fracture risk. Heavy alcohol intake likewise. Long-term use of certain medications - corticosteroids in particular, and some others - affects bone significantly enough that it changes screening recommendations. Very low body weight and prolonged low energy availability are also risk factors, which is relevant to anyone under-eating while training hard.
Knowing your actual numbers. If you are postmenopausal, have a family history of osteoporosis, have had a fracture from a minor fall, or have any of the risk factors above, a DEXA scan gives you a baseline rather than a guess. The practical value is that it changes the programme - someone with a normal scan can hop and lift heavy with ordinary caution, while someone with established osteoporosis needs a supervised and modified approach. Building a programme without knowing which of those you are is the main avoidable risk in this whole area.
A note on what happens if you stop. Bone adaptation is reversible. Density gained through loading is lost again when the loading stops, on a similar timescale. This is not an argument against starting - it is an argument for choosing a form of training you can sustain for years rather than an intensive block you will abandon.
This is general information, not medical advice. If you have been diagnosed with osteopenia or osteoporosis, have had a fragility fracture, or take medication affecting bone, get your programme built with a physiotherapist or exercise physiologist rather than from an article.
FAQ: Exercise and Bone Density, Answered
So should I stop walking?
No. Walking is genuinely valuable for cardiovascular health, weight management, mood, and joint health, and it supports balance. It is simply not a bone-building stimulus, so it needs something added alongside it rather than replacing.
How heavy is heavy enough?
A load where the last one or two repetitions of a set of six to eight are genuinely difficult while your form holds. If you finish a set feeling like you could have done another five, the bone stimulus is likely below threshold.
How long before a scan shows a difference?
Six to twelve months at minimum, and annual scanning is the usual interval because more frequent measurement cannot reliably distinguish real change from measurement error. Use strength gains as your short-term feedback.
Is it safe to jump if I have osteopenia?
Often yes, with a graded start, but this is exactly the situation where an individual assessment is worth it. Osteopenia covers a wide range, and where you sit in it changes the answer.
What if I only have 20 minutes twice a week?
Squat, hinge, and overhead press, three sets of six to eight each, heavy. Plus 20 heel drops daily. That covers the majority of the available benefit in the minimum time.
TL;DR:
- Bone responds to loads above what it is used to, applied fast - walking is already the habitual load
- Resistance training at genuinely heavy loads for 6-8 reps is the best-supported intervention
- Bone adapts only where it is loaded: squat and hinge for hip and spine, pressing for wrist
- Impact saturates fast - 10-20 hops or heel drops daily beats long jumping sessions
- Protein, vitamin D, and balance training all matter; get a DEXA baseline if you have risk factors
Walking is not the problem - believing it covers bone is. Add two heavy sessions a week and two minutes of heel drops a day, and you are doing something your skeleton can actually respond to.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
